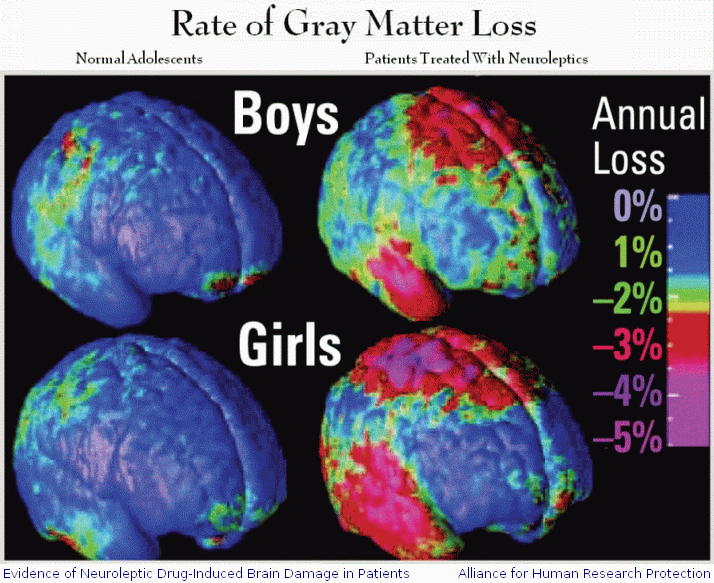Psychiatric Drug Facts via breggin.com :

“Most psychiatric drugs can cause withdrawal reactions, sometimes including life-threatening emotional and physical withdrawal problems… Withdrawal from psychiatric drugs should be done carefully under experienced clinical supervision.” Dr. Peter Breggin
Showing posts with label Human Experimentation. Show all posts

Apr 25, 2014

Dr. RICO Child Psychiatrist

updated April 25, 2014 first published May 20, 2012


Dr. RICO
Racketeer Influenced and Corrupt Organizations Act

I am disappointed by the lack of integrity that permeates the psychiatric profession. I see no evidence of any effort to be responsible or accountable for the harm done to patients. Bio-medical psychiatry has a foundation reliant on dishonesty. Psychiatrists who falsely reported of research results, fraudulently obtained FDA approval for drugs, and participated in illegally marketing of psychiatric drugs, help formulate public policy. It is plain that these psychiatrists are continuing to participate in what is a widespread ongoing criminal enterprise that continues to pick America's pocket and continues to harm thousands of patients. These doctors see nothing wrong with failing to warn other professionals away from corrupt 'evidence.' Psychiatrists don't petition medical boards to take away the medical licenses of the criminals among the APA and AACAP membership who have lied about 'the medicine;' not even those who have disabled and killed patients in drug trials and clinical practice. Doctors who buried the evidence of their wrongdoing, along with the bodies of their patients are considered 'Key Opinion Leaders.' Some are teaching in Institutions of Higher Learning using texts filled with their corrupt work. Discredited and fraudulent research remains in psychiatry's so-called 'Evidence-Base.' Coercive and manipulative social control strategies are standard clinical practices; this is social/political control by use of torture under color of law; if psychiatry is in fact an ethical medical specialty, I'm Mary Poppins...


At a Senate hearing that took place on December 1, 2011 Senator Tom Carper said the hearing was the culmination of the third investigation into the prolific use of psychiatric drugs particularly those prescribed off label then fraudulently billed to the Federal Medicaid program. What I want to know is WHY has there been no effort to prosecute obvious criminal activity, or better yet, STOP unethical pseudo-medical, i.e. fraudulent, standard practices? Psychiatrists adopting the bio-medical model by a political process have effectively functioned as social architects who willingly partnered with pharma and sold out their patients for financial and academic reward. Don't fool yourselves, psychiatrists are acting as eugenicists; psychiatrists have abused medical privilege, forgot ethical medical principles, lied about what is and is not known about psychiatric diagnoses---it is not the first time psychiatrists have done this. Psychiatrists have blatantly lied about the efficacy and the safety of prescribed drugs and their direct teratogenic mechanisms of action...Apparently lacking insight into the horrific human toll of their professional conduct, blinded to the iatrogenic harm inflicted on their patients, seemingly, absent any ability to truly empathize with or understand the meaning and the nature of their own tortured patients; psychiatrists determined by consensus that what they BELIEVE to be true about their patient is a fact, regardless of what their patient states. No need to ask the patient if they feel "effectively treated;" unless of course the patient is treatment compliant, i.e. successfully treated...

Somehow shared opinion is magically transformed it into scientific evidence by psychiatry. This 'evidence' is used by psychiatrists to 'practice medicine,' abusing their medical privilege to have noncompliant patients adjudicated as mentally ill in Courts of Law; while using subterfuge and coercion as 'medical instruments.' Psychiatrists are doctors treating 'brain diseases' but are not honest with their patients or the general public. Psychiatrists do not conform to ethical medical standards and violate the Human Rights of their patients as a matter of course. As a result, Human Experimentation has become the Gold Standard in clinical psychiatric care standards. The vast majority of psychiatric drugs are prescribed to people on Medicaid. When prescriptions are not FDA-approved, they are "off-label prescriptions;" e.g. prescribed experimentally. If the prescription is not supported by DRUGDEX, or another compendium of approved drugs recognized by Medicaid, both the prescriber and the pharmacist who cause a claim to be submitted for payment to Medicaid, are filing a fraudulent claim, it's a crime. This criminal activity continues unabated, and continues to cost billions; the human toll is inestimable.

The APA and AACAP professional associations are not regulatory bodies, both appear to be unable to accurately assess any ethical deficits in the "science" or the "medical practice" of psychiatry.  Albert Einstein said, “You cannot solve a problem from the same consciousness that created it. You must learn to see the world anew.” Psychiatry's ethical failure is the antithesis to medicine in the Hippocratic tradition, made more pronounced by it's consistent failure to recognize or respect the human rights of psychiatric patients. It is indeed criminal medical negligence for an individual, let alone almost an entire profession to abdicate any and all responsibility for the iatrogenic harm done to psychiatric patients; patients who are disabled and killed, without regard for the fact disability and death are consistent, if not desired outcomes. Willful blindness to obvious iatrogenic harm done by psychiatric drugs, including homicide is evidence of psychiatry's non-medical nature. Thomas Insel crowing about the need for using psychiatry's "evidence base" and recommending psychiatry implement even more reckless prescribing "standards" through "Translational Science;" is indicitive that Insel doesn't seem to realize there has to be actual 'ethical, medical science' to translate.

In reality, any actual medical science is too often obscured with the APA's pseudo-democratic manner of gathering "evidence" to validate the APA consensus driven diagnostic and treatment standards. Consensus is no substitute for ethical medical research. The willful blindness to a wide variety of cognitive, neurological, and metabolic iatrogenic damage inflicted on psychiatric patients is compounded by the medical neglect of psychiatric patient's iatrogenic injuries. Society is paying for the mentally ill to be legally compelled to be "medically treated" with neuroleptic and other psychoactive drugs; sometimes in combinations known to be fatal. Psychiatrists recklessly abuse prescription privileges off label prescribing is NOT license to prescribe for no good reason, without any evidence.... Psychiatry's psychopharmacological pseudo-medical treatments with or without electro-shock are potentially fatal. The fact some people subjected to psychiatric treatment describe it as torture, should not be ignored. Far too many people "medically treated" in reality, have been tortured. One never hears of the APA or the AACAP validating survivors and victims of iatrogenic drug induced disabilities much less honoring the memory of victims of iatrogenic fatality.
 
Psychiatrists who willingly participated in research that effectively served as a marketing tool for pharma and published 'peer-reviewed' articles in support of marketing agendas are considered 'KOLs;' BMOC basically. The APA and the ACAAP membership fail to value ethical medical standards. As a whole, the profession has functioned without ethical integrity. Lead researchers have actively and passively participated in an ongoing criminal enterprise that is subverting science and defrauding the American people while using medical fraud as a standard clinical practice. It is little surprise that these geniuses who are so called KOLs are recommending that nothing in the practice of psychiatry change.

via AACAP The Academy of Child and Adolescent Psychiatry

FAQs on Child and Adolescent Depression

"What causes depression in children?

"Depression has no single cause. Both genetics and the environment play a role, and some children may be more likely to become depressed. Depression in children can be triggered by a medical illness, a stressful situation, or the loss of an important person. Children with behavior problems or anxiety also are more likely to get depressed. Sometimes, it can be hard to identify any triggering event."

The claim that depression is caused by a 'chemical imbalance' is no longer being made; paltry evidence of what should be a concerted effort to start providing factual information to the public. It is apparent to me that these professionals do not appear to concerned about regaining the public trust that has steadily eroded due to a serious lack of integrity in academic research, fraudulent marketing and abdication of ethical duty to patients. and . However, after reading this: "Are medications safe? Do they increase risk of suicide? When prescribed and monitored carefully, medications are both safe and effective ways to treat of depressed youth. Fluoxetine or Prozac, a selective serotonin reuptake inhibitor, is the medicine that so far has proved most safe and effective. There are times, however, when other medications can and should be used. While medications have been associated with a small increase in thoughts of suicide, there is no evidence that antidepressants actually increase the risk of suicide. For moderate to severe depression, the potential benefits from medication treatment seem to outweigh the potential risks. Click here for a complete discussion of the use of medication in childhood depression." I realized that no real changes are planned (to actually become ethical or evidenced-based medicine) Psychiatric drugs will continue to be recommended as a "First-Line" treatment for depression; and apparently, other drugs as well. I also realized (once again) that psychiatrists in positions of leadership at the ACAAP, seem to have no problem at all flat out lying about the drugs they are using.

The use of SSRI antidepressants on children and adolescents is based on the TADS Drug Trial. In the trial there were a total of 18 suicide attempts all but one was a kid who was on Fluoxetine, or Prozac, and there was an obvious attempt made by the researchers to present the data in a way that would misrepresent the suicide data in journal articles. Robert Whitaker reported, "The TADS study has been used to justify the prescribing of Prozac—and really, by extension—other SSRIs to children and adolescents. The TADS researchers reported that the drug treatment was effective and didn’t increase the risk for suicidal events, as compared to placebo. Adding CBT to medication “enhances the safety of medication,” the TADS researchers wrote.

"All the while, the real suicide data was being hidden. The TADS investigators weren’t disclosing the number of suicide attempts, and they weren’t reporting that all but one of the suicide attempts were in fluoxetine-treated youth. Instead, they made it appear that a similar number of suicidal events had been seen in the placebo group, and, at one point, even wrote that 15 in this group had attempted suicide." read here

Dr. David Healy reports, "The FDA became party to a myth that somehow Prozac was ok where other antidepressants given to children weren’t.

"Because FDA had licensed Prozac for depression before the 2004 suicide controversy blew up, they became party to a myth that somehow Prozac was ok where other antidepressants given to children weren’t. Prozac in fact shows no more efficacy than other antidepressants for children and has just as bad a suicidality profile, along with a range of other harms such as sexual dysfunction, inhibited growth, and other problems, as other antidepressants. emphasis mine

"This is not an argument against Prozac. Suicidality can be anticipated and forestalled by warning patients. I once thought that an appeal to patient safety would get doctors on board." here

In a large NIMH trial of 4,041 “real-world” outpatients, only 108 patients remitted and stayed well and in the trial during the one-year followup. Efficacy and Effectiveness of Antidepressants. Pigott, H. Psychotherapy and Psychosomatics, 79 (2010), 267-279.

Retract Study 329 from 1Boring Old Man

photo credit sciencephoto.com

Mar 7, 2013

Antipsychotic Use by Medicaid-Insured Youths: evidence of criminal prescribing practices


Average rate of gray matter loss: evidence of neuroleptic drug-induced brain damage.
The more drugs you've been given, the more brain tissue you lose. What exactly do these drugs do? They block basal ganglia activity. The prefrontal cortex doesn't get the input it needs and is being shut down by drugs. That reduces the psychotic symptoms. It also causes the prefrontal cortex to slowly atrophy. 
~ Dr. Nancy C. Andreasen, New York Times, Sept. 16, 2008

Both the older and the atypical neuroleptics shrink brain tissue during routine clinical exposure.
~ Dr. Peter R. Breggin, Brain Disabling Treatments in Psychiatry (2008) 

ARTICLES   |    
Antipsychotic Use by Medicaid-Insured Youths: Impact of Eligibility and Psychiatric Diagnosis Across a Decade
Julie Magno Zito, Ph.D.; Mehmet Burcu, M.S.; Aloysius Ibe, Dr.P.H.; Daniel J. Safer, M.D.; Laurence S. Magder, Ph.D.
Psychiatric Services 2013; doi: 10.1176/appi.ps.201200081
Author and Article Information
Dr. Zito and Mr. Burcu are affiliated with the Department of Pharmaceutical Health Services Research and Dr. Magder is with the Department of Epidemiology and Public Health, University of Maryland, 220 Arch St., Room 01-216, Baltimore, MD 21201 (e-mail: jzito@rx.umaryland.edu).Dr. Ibe is with the School of Community Health and Policy, Morgan State University, Baltimore.Dr. Safer is with the Department of Psychiatry, Johns Hopkins University, Baltimore.
Copyright © American Psychiatric Association
a couple of excerpts:
Conclusions
"The expansion of antipsychotic medication use from 1997 to 2006 among Medicaid-insured youths was most prominent among those qualifying with low (SCHIP) and very low (TANF) family incomes. This was the case even though the most impaired youths—those in foster care or those receiving SSI—had distinctly higher levels of antipsychotic drug use within each study year. Factors contributing to this antipsychotic use pattern included the expanding SCHIP and TANF populations, the increased use of antipsychotics among youths enrolled in SCHIP and TANF, and the increased use of antipsychotic medication for behavior disorders over the decade. Likewise, although youths with diagnoses of schizophrenia and other psychotic disorders and pervasive developmental disorders had the highest rates of antipsychotic medication use, youths with externalizing behavior disorders far outnumbered those with these less common conditions and constituted the largest group of utilizers of antipsychotic medications."
"Methods: The authors analyzed computerized administrative claims data for 456,315 youths aged two to 17 years who were continuously enrolled in Medicaid in a mid-Atlantic state in 1997 (N=159,171) and 2006 (N=297,144)."

In 1997 a total of 615 kids with no diagnosis were prescribed neuroleptic drugs in this sample. More than twice as many kids, a total of 1,481 were prescribed a neuroletic drug in 2006, despite the fact they had no psychiatric diagnosis which would indicate a need for such a prescription!

What the above represents is only a small percentage of the number of fraudulent claims which were submitted to Medicaid for payment, i.e. fraud. Obviously, the civil and criminal penalties paid by the pharmaceutical industry for illegally marketing these drugs is not going to stop the fraud. The unethical medical practitioners are defending their "professional privilege" to use these drugs absent evidence the drugs "treat" the conditions the drugs are prescribed off label for. It is the prescribers whose unethical prescribing of these teratogenic drugs to children are guided by the APA and AACAP practice parameters and treatment algorithms who must be stopped.  Standard practices originally protected patients, now they serve to protect the unethical behavior of the professionals who use them as an affirmative defense for what is not only medical malpractice, but Human Experimentation; the current standard in mental health care for kids on Medicaid.  


hat tip: Allen Frances, M.D.


House Hearing,  2009

Special thanks to Methodius Isaac Bonkers of Bonkers Institute of Nearly Genuine Research for the graphic and the quotes at the beginning of this post.


FAIR USE NOTICE: This may contain copyrighted
(C) material the use of which has not always been specifically authorized by the copyright owner. Such material is made available for educational purposes, to advance understanding of human rights, democracy, scientific, moral, ethical, and social justice issues, etc. It is believed that this constitutes a 'fair use' of any such copyrighted material as provided for in Title 17 U.S.C. section 107 of the US Copyright Law. This material is distributed without profit.

Nov 5, 2012

Without justice, society elevates criminals into virtual Masters over their victims


I guess that rumor that Washington State is going to get rid of the MPC providers  may have been true...I wonder if it is because they won a Lawsuit against the State.  MPC providers are owed back pay with interest. Washington State has ignored the  2007 Washington State Supreme Court Jenkins v DSHS decision the entire time I have been my son's provider, I am owed a few grand in back pay myself...

The Department ignored several Court Orders to act on Isaac's behalf when I brought him home from Child Study and Treatment Center when he was almost 17 in 2005. 
It's how DSHS "does business."


I am utterly disgusted with the behavior of the local Home and Community Services,HCS, and SE Washington Aging and Long Term Care, ALTC. The statements and the actions of Dirk at HCS and the ALTC staff are defamatory and slanderous. Once I had faxed my hand written affidavit correcting the BCCU report which states I had answered question 13 with a "yes," I contacted the ALTC office to be informed by Jackie Klingle that a determination had been made that I am no longer allowed to be Isaac's care provider. She refused to give me any reason whatsoever for the determination. Question 13: "Have you ever has a contract and/or license to care for children, juveniles, or adults denied, terminated, revoked, relinquished, or suspended?"

I was first made aware that there was a problem on the 30th of October when a potential in-home care client called me and told me that Dirk at the Home and Community Care office had called her and told her that I could not be her care provider because my license was revoked due to committing  a crime. I knew that this was not true, and I am horrified that such a thing was told to a potential client. There is no excuse for such unprofessional conduct. I turned in a background authorization to the ALTC office and one to the HCS office on the 24th of October. The ALTC BCCU report is dated the 25th, and there is a note written on it that says, "11/17/2006 Wapato HCS" next to the highlighted statement that I answered "yes" to question 13.  I became Isaac's care provider in 2008, and the BCCU report dated 11/25/2008 makes no mention of question 13.  The HCS ran their report on the 26th. It is more than a little suspicious that in the 4 and 5 day interim between the reports being printed and Dirk slandering me to a client, neither agency made any effort to contact me. 

On the 30th I went to the HCS office to speak to Dirk who was less than polite. He proceeded to tell me three different stories as to why I was not going to be allowed to be a care provider for a potential client who has a care assessment for 29 hours of assistance a month. First, Dirk stated I had been terminated because of my 1994 conviction for 4th degree assault. When I informed him that I knew the conviction was not a disqualifying crime, he then claimed I was disqualified because the BCCU report which states that I had answered "yes" to question 13. It was this second story that made me realize he was lying and he was pissed as hell, although entirely calm. So I pointedly asked who he was and asked him why he had failed to even introduce himself. Pointing out his rudeness, made him angrier. The man did not introduce himself, and he was rude and condescending---it was entirely obvious that he had no respect for me whatsoever; it was equally obvious that he felt no need to hide his contempt. Ultimately, he seemed to become be even more unhappy when I pointed out that he had not even bothered to do any fact checking; and as a result he had stated things which he did not know to be true, that in fact are not true. He did not appreciate me pointing out his blatantly unethical behavior. I asked him if he thought there was anything wrong with telling a client that I had lost my license, when this was not a fact he knew to be true. He said he didn't. It was then that Dirk told me the third story he offered as a reason for terminating my contract. Derik stated that I can not be a provider because my birth mother's ALTC case manager (I forget her name) put me on a Status 4 list(whatever that is).  He told me that he had been reading a report that said I had abandoned my birth mother when I was her in-home care provider, and that I had robbed her and left her barefoot at the mission. These are spurious allegations, and Dirk basically sneered at me while he spat out that he had been reading how I had allegedly committed horrific crimes including abandonment when he was told I was at the HCS office to see him. If this were true why was there no criminal complaint filed with Law Enforcement as required by Law? There was no criminal investigation or prosecution. I was never served with any legal notice that the Department had done an investigation or that the Department had substantiated any of what Dirk told me my birth-mother's ALTC case manager had allegedly reported. I've never been served with any legal notice that a determination has been made which disqualifies me from being a care provider.  

I am sick and tired of DSHS employees who are unethical, dishonest and disrespectful and who abuse their authority with impunity. I am tired of being disrespected and treated as if I am not a human being worthy of respect, but after twenty years, I'm used to it---I figure the fact it still makes me sick, is a good thing. At least I know it's wrong; and I don't have Stockholm syndrome. But this is not about me, or how I have been repeatedly traumatized; it is about my son, Isaac and the countless felony and misdemeanor crimes, ethics violations committed by public servants whose unprofessional behavior and rude disrespectful treatment repeatedly traumatized my son and put him in harm's way again and again. This is about State employees and contracted "care" providers who abuse their authority with impunity due to a lack of accountability that is the accepted norm in the unethical culture entrenched within publicly funded child welfare, mental mental and social service programs. This is about the abject failure to protect or defend children and vulnerable adults who are victimized. 

I find it truly ironic that not once has anyone been held accountable in 20+ years for crimes committed victimizing my son, Isaac. No matter the crime, whether it be assault, battery, medical neglect, using perjury to civilly detain and commit him, or using him in human experimentation---which he described as being tortured. My son thought he'd been kidnapped; and in effect, he was. Washington State made him a Ward of the State in order to claim Federal Child Welfare funds; it's called fraud.  DSHS has repeatedly violated my son's Civil Rights, and has repeatedly violated my Civil Rights, for over twenty years. I want to know why in the hell is it permissible for DSHS to violate the Law, and violate my son's Constitutional Rights on a regular basis, ever since he was beat up and put in a closet while in a foster care when he was three years old? I want to know why it is permissible for numerous Case Workers and mental health "professionals" to perjure themselves in Superior Court? Tracy Dalton in King County, Doug Savelesky, Nancy Sherman, and Jeffrey Jennings, in Yakima County, and Leah Landis in Pierce County these are State employees and mental health professionals who perjured themselves in the last 17 years in Washington's Superior Courts while acting as agents of the State of Washington, Under Color of Law. Gary Peterson lied and cost the State $30,000; he experienced no consequences and was allowed to abuse his authority to punish us over and over again...The Medical Director of CSTC, Jon McClellan, tortured my son; treated my son as if he were a lab animal in Drug Trials. In doing so, he broke State, Federal and International Law. He ultimately "treated" my once brilliant son into a state of profound iatrogenic disability. He is still the Medical Director of CSTC; he is still teaching at UW; and most of all, he still belongs in a Federal Prison. 

The cock and bull story alleging that I have been terminated as a care provider because I allegedly committed heinous crimes that were never reported, investigated or prosecuted is particularly cruel all things considered. 

My hope is that writing about these events will compel others to act on the knowledge that public employees and contracted "care" providers must be accountable for violating the law. If public employees abuse the authority vested in them by society, they must be held accountable by society. If they commit crimes, they must be criminally prosecuted. It is not possible to act in the "best interests" of vulnerable children and adults by committing crimes and being deceitful; it does not serve the public good to allow such criminal behavior to go unpunished. Without justice, society elevates criminals into virtual Masters over their victims, while leaving their victims defenseless. Society becomes complicit by remaining silent. Public employees who are not accountable will victimize those we entrust them to serve with impunity. 

Sep 30, 2012

Priceless...


A thirty day supply of the 4 teratogenic psychiatric drugs my son takes: $1,124.17

Number prescribed for Tardive Dyskinesia?: 1

Number of prescriptions taken daily known to cause iatrogenic injuries and cognitive impairment: 4

Number of drugs that were FDA-approved for pediatric: Zero.

Number of prescription drugs my son takes that the FDA has since approved for use in children 13 and older?: 0

My son was further victimized, traumatized and ultimately disabled by a doctor who acted with impunity; he abused my son, abused his medical authority, and disregarded medical ethics altogether.   More than a million dollars was stolen from the American people by the Children's Administration employees of Washington State that intentionally defrauded Federal programs by making my son a Ward of the State. In effect, public servants robbed my friends, my neighbors and my family to pay for what was done to my son. Knowing that I was deprived of my Constitutional Rights as a parent, and was not allowed to protect my own son is something I cannot forget. Knowing I was deprived of my parental rights to act in my son's best interest and make medical decisions on his behalf without Procedural or Substantive Due Process of Law by Jon McClellan. Aresearch psychiatrist and the medical director of CSTC said he didn't need my Informed Consent. A coerced assent from my traumatized child? Absolutely priceless!

This is a MadMother MasterCard moment...


I was told if I didn't sign A Consent to Place agreement, I would be portrayed by the State as being unwilling to ACT IN MY SON'S "Best Interests." There was a Team Child Attorney who had been involved for years--whose Federal mandate is to preserve and defend my son's Constitutional Rights as a disabled child; another Officer of the Court who failed their duty to my son...When I asked why can't the real reason for the Consent to Place Agreement (to provide for my son's medical care due to being beat up and put in a closet and never receiving the recommended treatment for his traumatic injuries) be stated on the petition; I was told that was not allowed!  They ALL knew what was being done was ILLEGAL and advised me to go along with it, or "it would make me look bad." Years later, I learned that day, at that hearing was the ONLY opportunity the Law allowed for me to state for the record the facts which the "professionals" said couldn't be used...My Attorney failed to advise me of my right to do so; in fact he advised I just go along or the State would make me look bad...I was assured that I retained my parental rights to provide Consent to all Medical Treatment for my son...Those parental rights are now, and were then, preserved according to State and Federal Law.  

I'm not the one who looks bad. I'm not an Officer of the Court. I have never perjured myself in a Court of Law. I learned what my rights are; I researched dependency and mental health law; and learned what Court Procedures needed to be followed and suuccessfully sought my son's release from a locked psychiatric facility. By the Grace of God, I finally brought my son home January 5, 2005. 

All I had was the Law, the truth, and a naive belief that in a Court of Law, the law and the truth are all that is required...

original June 2011 updated for accuracy

Jun 23, 2012

Dear Dorktor, psychopharmacology as it is practiced, is not ethical medical care


How and why mainstream psychiatry became psychopharmacology had nothing to do with what was in the best interests of psychiatric patients. I say this, because it is apparent to me that in the disease model, that psychopharmaocology is based upon, the patient's subjective experiences, are minimized or dismissed altogether. No man is an island. Emotional, psychological, social, and behavioral factors and symptoms do not develop in a biological vacuum; human beings are not simply biological organisms. For so-called 'experts' to be certain of their ideas to the degree that ‘psycho’ pharmacologists seem to be, absent definitive empirical evidence that even supports, let alone scientifically validates these ideas, is sheer lunacy. If symptoms could be best understood solely within such a biological framework, wouldn't that just be marvelous? (I am being sarcastic)

A common self-defense used by parents of adults labeled with psychosis is that they did not abuse their offspring, they didn't cause their child to have "schizophrenia." Apparently, it's considered an insult or perceived as some knid of threat to some parents of minor and adult children with psychiatric diagnoses to suggest that a loved one's symptoms are not caused by an illusory brain disease; but may be described as coping strategies resulting from unresolved intra-personal conflicts and/or conflicts within relationships. This explanation is  frequently perceived by family members as an accusation, accompanied by a judgment that assigns blame.

I don't personally believe that truly accepting personal responsibility for how our behavior affects others means that we are "to blame" for a person having a "mental illness." I know that how we treat people, whether they have a psychiatric diagnosis or not, always matters--we affect one another. The disease model relies on the assumption that how we treat one another has nothing, or very little, to do with people developing symptoms of "mental illness."  I don't buy it, for even a fraction of a second.

Ironically, some of the parents who are faithful believers in the neuro-biological disease hypothesis have no difficulty describing how they themselves are adversely affected by a mentally ill family member's behaviors, symptoms, understandably, some resent the adoption of a care-taking role.  People who have no difficulty stating that they experience symptoms of depression, anxiety, etc. that they then attribute to being the parent and/or the caretaker for a person with a psychiatric diagnosis. These family members cast themselves as victim/martyrs who can't cause "mentally illness," because it's a "brain disease." While they are motivated by love, they are limiting their potential to be helpful to their loved one, and perhaps preventing a more thorough of their loved one's distress. How is it possible to effectively support and/or advocate FOR a loved one without considering how one treats a family member who is in distress important? How we treat a person with a psychiatric diagnosis can exacerbate or relieve symptoms.  How can anyone act in the "best interests" of a family member without being willing to thoroughly explore how family dynamics and one's own responses may cause additional distress and exacerbate a loved one's symptoms? Ironically, some family members seem to believe themselves to be only a positive influence in a loved one's recovery...

In the disease model, the patient is effectively invalidated, and discounted as a matter of course; this utterly and completely disrespectful treatment frequently serves to exacerbate symptoms of distress, breeding misunderstanding, causing mistrust. In my experience, people who are experiencing psychosis, have little difficulty in discerning when others are being disrespectful, judgmental and have little regard for them. Conversely, people experiencing psychosis can invariably discern when others are supportive, kind and who truly value them as a human being, worthy of respect and validation.

The disease model effectively invalidates a person instead of seeking to understand their experiences, perhaps to understand how these experiences have caused the symptoms of their distress. Psychophamacology seeks to extinguish psychosis with seemingly little consideration given to how the neurotoxic drugs affect the whole person by chemically altering biological processes in very meaningful, and an extremely deleterious manner. To focus on the chemical biological processes, which are not clearly understood; by using teratogenic drugs which alter even more biological processes than are intentionally targeted; and claim that this is based on medical science, and that it is effective treatment is dishonest to say the very least! Given what is now known about the the etiology of mental illnesses, and the action of the teratogenic drugs used to treat them, it isn’t even ethical to use them without fully informing the people that using them is in reality, Human Experimentation, as their use is not based on the scientific evidence, but the subjective opinions and observations of so-called ‘experts.’

How in the hell can altering normally functioning biological processes and causing cognitive and neurological impairments and physiological systems to dysfunction be considered ethical, medical treatment? It is sheer hubris to believe iatrogenic harm is justifiable or therapeutic.

I just don't get it. I have always been interested in what makes people think, feel and behave the way we do. I like to think I have a pretty decent grasp on why humans develop in the manner we do, and what it requires to develop into healthy functional adults. I simply do not understand how or why a profession whose mission is to heal to understand, diagnose and treat the minds of those with a mental illness, could come to rely on a yet to be validated hypothesis, and arrogantly assume that a belief in a yet to be validated hypothesis, can be the foundation of Evidence-Based treatment for a disease not yet identified much less, understood.

"Psycho" pharmacology is not effectively treating many patients; but is instead disabling and killing children, traumatized veterans and the elderly at an alarming rate.

May 1, 2012

Plan to monitor ongoing harm done to foster children

DSM-1, 1952: 106 disorders
DSM-II , 1968: 185 disorders
DSM-III, 1980: 265 disorders
DSM-IV, 1994: 357 disorders

It appears that the Administration on Children, Youth and Families, 'ACYF' plans to continue allowing children in foster care to be drugged with psychiatric drugs even though there is ample evidence that this Standard Practice is not 'effectively treating' the psychiatric diagnoses the drugs are prescribed for.  The standard clinical practice of using teratogenic psychiatric drugs is not based on sound ethical medical principles, and is not supported with definitive empirical data showing the drugs to be safe or efficacious for use on children.  Using drugs which are not efficacious, that are known to be dangerous teratogens with fatal risks, without scientific evidence to validate the practice,  is Human Experimentation.  The plan to 'monitor' and provide 'oversight' of psychiatric drugs being used in what is essentially Human Experimentation on vulnerable foster children does not protect the children from further harm; this is a poor plan to say the very least...

This is not something that needs Federal 'oversight,' nor does it need to be 'monitored.' 
IT NEEDS TO BE STOPPED!

via The Policy Lab at The Children's Hospital of Philadelphia

April 30, 2012

New PolicyLab Research Expands Understanding of Psychoactive Medication Use Among Children in Foster Care

A few months after the federal Government Accountability Office (GAO) issued a report on the use of psychoactive drugs by children in foster care in five states, a national study from PolicyLab at The Children’s Hospital of Philadelphia describes prescription patterns over time in 48 states. The updated findings show the percentage of foster children taking antipsychotics--a class of psychoactive drugs associated with serious side effects for children-- continued to climb in the last decade. At the same time, a slight decline was seen in other psychoactive medication use, including the percentage of children receiving three or more classes of these medications at once (polypharmacy). here


via PR Newswire:
PRESS RELEASE
New research expands understanding of psychoactive medication use among children in foster care
a few excerpts:
"We're not saying these medications should never be used for children, but the high rate at which they're used by children in foster care indicates that other interventions and supports, such as trauma-based counseling, may not be in place for them. In other words, health care providers may not have other, non-medication, tools to offer families dealing with mental health concerns," said Rubin. "Responding to high and growing levels of antipsychotic use will not simply require efforts to restrict their use, but calls for larger investments in mental health programs that help these children cope with trauma psychologically."
"Prescription rates for both antipsychotic use and polypharmacy varied widely from state to state. Over the six-year period, antipsychotic use increased in all but three states. Conversely, 18 states showed an increase in polypharmacy, while 19 states showed decline and 11 no change. In 2007, states reported prescriptions of antipsychotics ranging from 2.8 percent to 21.7 percent of the foster care population, and from 0.5 percent to 13.6 percent for children receiving multiple classes of psychoactive drugs. The authors note, however, that it's not possible to use this study to compare states against one another.
"In illustrating both the national and state-specific trends in the use of psychoactive medications over time, we hope to provide a resource to officials at both the federal and state levels to help identify progress and prioritize intervention areas," noted Meredith Matone, MHS, a research scientist at PolicyLab who co-authored the study currently published online in the journal Children and Youth Services Review.
"Bryan Samuels, Commissioner of the Administration on Children, Youth and Families (ACYF), said "the study's findings contribute to ongoing Federal efforts to improve the oversight and monitoring of psychoactive medications by providing a new snapshot in time on how these drugs were used in almost every state in the nation." ACYF, part of the U.S. Department of Health and Human Services, works across federal agencies and with the States to use the latest data and research to design and deliver the best health care services for vulnerable children.(emphasis mine)
"In August, ACYF will bring child welfare, mental health, and Medicaid leaders from all 50 States, DC, and Puerto Rico together to address the appropriate use of psychoactive medications in state foster care programs." read here

Big Bucks Big Pharma


picture bonkersinstitute.org

Apr 27, 2012

Who will stand up for the children like Herbert Coley has for our Soldiers?

via nextgov.com

Flickr user deanslife
This is the sixteenth story in an ongoing series.
The Army Surgeon General's office is backing away from its long-standing endorsement of prescribing troops multiple highly addictive psychotropic drugs for the treatment of post-traumatic stress disorder and early this month warned regional medical commanders against using tranquilizers such as Xanax and Valium to treat PTSD.

An April 10 policy memo that the Army Medical Command released regarding the diagnosis and treatment of PTSD said a class of drugs known as benzodiazepines, which include Xanax and Valium, could intensify rather than reduce combat stress symptoms and lead to addiction.
The memo, signed by Herbert Coley, civilian chief of staff of the Army Medical Command, also cautioned service clinicians against prescribing second-generation antipsychotic drugs, such as Seroquel and Risperidone, to combat PTSD. The drugs originally were developed to treat severe mental conditions such as schizophrenia and bipolar disorder. The memo questioned the efficacy of this drug class in PTSD treatment and cautioned against their use due to potential long-term health effects, which include heart disorders, muscle spasms and weight gain. here

About time someone had some sense!   Thank you Herbert Coley for acting on behalf of our men and women in the Military!

Now let's see someone, like Senator Tom Carper raising the alarm and putting a stop to drugging our children with the very same highly addictive psychotropic drugs!  Haven't heard a peep about any follow up to the investigation into the drugging of children or the Senate hearings conducted on December first.  This is the third investigation into the harm being done to children by psychiatric drugs.  How many times do we need to quantify the fraud and corruption being committed in order to do serious harm to children by giving them teratogenic psychiatric drugs?  Where is the effort to stop what is in fact, widespread Human Experimentation on children?  Given the actual death and disability rates; The American people are literally paying for hundreds of thousands of children to be permanently disabled and killed--because they are poor, and on Medicaid.  It's 'just business' for the Big Pharma and the bio-maniacs into 'psycho' pharmacology.  

I didn't deal with Corporate Pharma, so my anger is for the so-called doctors who are academic research psychiatrists.  These so-called experts have aided and abetted in perpetrating a massive fraud---it could not have been done without their expert opinions...The Key Opinion Leaders, "KOL"s, who are the Who's Who of Academic Fraud---have not been honest, and did not have to SHOW their WORK, to be considered 'lead researchers.'   It is now well known that the benefits of the drugs were largely illusory and exaggerated, and the risks were denied or minimized. Psychiatry, specifically, 'psycho' pharmacology, has a seriously corrupted 'evidence-base.'  As a result, many standard 'treatment protocols' and 'algorithms' and Practice Parameters used in clinical practice have little to NO scientific validity---particularly, the practice of prescribing neuroleptic and other neuro-toxic psychiatric drugs to children for behavioral problems----These drugs have the risks of disability and death, and in the case of the neuroleptics, or 'antipsychotics,' it is more a question of when, not if, a child or adolescent will experience deleterious effects from the drugs. 

Jon McClellan testified on December 1, 2011 at a hearing about the use of psychiatric drugs in foster children; which is only part of the story.  See What were the parents of 18,800 children told?  He also wrote a document which estimates 50% of children given neuroleptic drugs will develop Tardive Dyskinisia, a neurological condition which can be disabling and permanent--even if the child stops taking the drug.  Where the figure comes from is not cited, but these drugs have been used for decades.  So it is strange that Jon McClellan did not seem alarmed at all when he testified as an expert witness that drugs he has authoritatively stated will cause half of the kids who take the drugs to develop a neurological impairment which can be permanent, are now in widespread use 'off-label'!  The neuroleptic, or 'antipsychotic' drugs alter the function of every major physiological process...Digestive, metabolic, cardio-vascular, neurological, endocrine, or hormone system; in fact the entire parasympathetic nervous system can be altered, not correcting an identified dysfunction but causing dysfunction.  These drugs are minimally effective for a small percentage of children diagnosed with the conditions for which they were intended and FDA-approved to treat.  Why are we allowing children to be given these teratogenic drugs in the absence of sound scientific reasoning, sound clinical judgement, and in violation of the Hippocratic Oath, the Ethical Guidelines for Informed Consent and the Nuremberg Code?  Make no mistake, 'off-label' prescriptions which are not supported by empirical data and---anecdotal evidence alone is not a substitute---without empirical evidence of either safety or efficacy to validate the 'off-label' prescribing of psychiatric drugs, it is in fact, experimental.  

It is Human Experimentation on children. 
It is is not something that needs to be regulated.
IT NEEDS TO BE STOPPED.  

Mar 17, 2012

Parents: Please Educate Yourselves About Psychiatric Drugs


What is the Scientific Basis of Psychiatric Treatment?
PLEASE EDUCATE YOURSELF ABOUT PSYCHIATRIC DRUGS

According to the Wall Street Journal 6.5 million children and youth 19 and under given neuroleptic drugs, called 'antipsychotics' in 2009. I wonder how many of these children experienced a life threatening emergency, became disabled, or died as a result? The lack of honesty is seemingly endemic to psychiatric research and 'peer-reviewed' professional journals, psychiatric textbooks and Continuing Medical Education programs. Since this corrupted "Evidence Base" is what 'mental health treatment' is based upon, checking facts about the risks associated with taking psychiatric drugs is not only advisable' it's a necessity. The Physicians Desk Reference,  The Alliance for Human Research Protection, and RxISK.org are some of the sources available online.


KIDSMEDSWEB


The reality is used as directed, neuroleptics, called 'antipsychotic,' drugs, can cause illness, disability, brain damage and early and/or sudden death. The fact that these very real adverse effects are NOT being shared with people prior to the drugs being prescribed to them, is obviously unethical; it is also criminal. When these teratogenic drugs are prescribed to children, (usually "off-label") parents are often not even informed of the very real life-altering conditions that are drug-induced, commonly occur, even though these adverse effects can be disabling, and even fatal. neuropleptic drugs are commonly prescribed "off label" an innocuous term that belies the fact that using the drugs in this manner is in fact, "experimental use" of very dangerous drugs. It is human experimentation; the fact that it is being done in standard clinical practice,is evidence that psychiatry is not in fact "evidence-based." There isn't sufficient empirical evidence to support using neuroleptic drugs "off label" for any condition or behavior any child has; in reality, the empirical evidence is not robust enough to consider neuroleptic drugs as a first-line treatment for childhood-onset schizophrenia.

Parents are not being told that there is often little, to no evidence to support many prescriptions for psychotropic drugs; nor are they given accurate information about the direct adverse effects of the psychiatric drugs prescribed to their children. Not being given the facts, undermines a parent's ability to make informed decisions in their child's best interest. In reality, it often means that parents are not being given the information necessary to determine whether or not their child should take the drugs being prescribed. This ethical failure is not necessarily accidental or even an intentional oversight; it is more often due to the corrupted data that is contained in the evidence base. The average mental health professional who relies on the articles in peer reviewed journals cannot help but be misinformed and consequently provides patients and parents with biased, or otherwise inaccurate information about the drugs they recommend.

Marcia Angell, MD, former Editor in Chief of The New England Journal of Medicine, reviewed three important books that examine corporate-academic liaisons that have corrupted the integrity of American medicine. In her review titled, Drug Companies and Doctors: A Story of Corruption, she said of Jeffrey Biederman: "Thanks largely to him, children as young as two years old are now being diagnosed with bipolar disorder and treated with a cocktail of powerful drugs, many of which were not approved by the Food and Drug Administration (FDA) for that purpose."

"Between 2000 and 2007, Dr. Biederman was paid at least $1.6 million in consulting and speakers fees to promote the use of toxic drugs--in particular, antipsychotics--for children, for whom they had not been approved. The short-term harm produced by these drugs in children is documented--including obesity, new onset diabetes, and heart damage. The effect of long-term use of these drugs by children is still mostly unknown. However, the capacity for harm in particular for children's immature, still developing brains is immense...

"In spite of corruption, fraud, and invalidated research and unethical conduct; the work of Biederman, Nemeroff, and Schatzberg, (among others) remains intact in "peer-reviewed" journals and textbooks; and is used in clinical practice across the country. According to Dr. Angell, "Legally, physicians may use drugs that have already been approved for a particular purpose for any other purpose they choose, but such use should be based on good published scientific evidence." (emphasis mine)

I have questions for all psychiatric and mental health professionals, and so should any parent who seeks mental health care for their child. Here are a few of mine:

What is the scientific basis for using dangerous neuroleptic drugs, or "antipsychotics" for any diagnosis?

What is the scientific basis for using neuroleptics 'off-label,' i.e. experimentally, on children?

What is the scientific basis for coerced, i.e. forced or "assisted" treatment of any one?

Is dishonesty and abuse of power, i.e. the use of coercion, misleading patients/parents about the nature of a psychiatric diagnosis by stating it is a disease, 'chemical imbalance' or 'neurobiological' condition acceptable, or even ethical?

What is Informed Consent?

Is Informed Consent possible when professionals rely upon corrupted data and the biased articles in "peer-reviewed" professional journals that exaggerate the benefits and minimize the risks?


Informed Consent
Informed consent discussions should include disclosing the fact that all psychiatric diagnoses are based on subjective observation and opinion. The consent discussion should also include informing people of the life-altering risks to one's liberty interests once a psychiatric diagnosis is attached. The risks of the proposed treatment; and the potential benefit of the recommended treatment need to be understood. An ethical Informed Consent process cannot include manipulating the patient or family member in an effort to convince them to consent to treatment. Telling people that a psychiatric diagnosis is caused by an unidentified "disease" when no disease has been diagnosed or identified in the diagnostic process; it is dishonest and no professional should make a fraudulent claim to coerce the patient or a parent into believing a diagnosis requires "medical treatment." To use these tactics is to commit fraud, not provide ethical medical care. Making fraudulent claims is unethical, no medical professional should mislead and/or outright lie to a patient or their family members in an attempt to alter behavior to gain cooperation or treatment compliance. It is entirely unethical to coerce and manipulate a person while simultaneously limiting or inhibiting the person's ability to exercise their own free will, or in an attempt to alter their decision. Informed Consent can only be ethically obtained when valid accurate information about the diagnosis, and the recommended treatment, is understood by the person giving consent.  Consent is guided by a patient's self-determined morals and values and serves the self-identified best interests of the patient; informed consent must be freely-given.

Informed Consent requires honest forthright communication. It is an ongoing conversation about the risks vs. the benefits. Informed Consent is a decision made by the patient, or the guardian of the patient. All relevant information is (theoretically) provided by the prescribing professional. The discussion should include whether the drug prescribed is being prescribed for an FDA approved use, or is being prescribed experimentally. It is inaccurate and misleading to refer to these prescriptions as simply being "off-label."  I say this because "off-label" use is common in medicine, but it is still needs to be supported with evidence that using a drug "off-label" is safe and effective for the person and the condition for which it is being prescribed.  Rarely do "off-label" prescriptions have such evidence to support them. since these types of prescriptions are not supported with empirical evidence of either the safety or effectiveness and the potential risks include dependence, iatrogenic disability and death.

Alternative treatments, whether available or not, and no treatment, should be part of the consent dialogue. A professional should be supportive of the patient and/or parent who needs time to digest the information shared, and supportive if they wish to consult anyone they choose before making a decision.  These are requirements in the American Medical Association's Ethical Guidelines for Informed Consent.

The choice to take or not take psychiatric drug/s as prescribed must be made freely, voluntarily, and without coercion; and without fear it will be disrespected or under the threat of filing a CPS report alleging medical neglect. Removal of children into foster care Under Color of Law by mental health professionals and child welfare workers has become an ever-present threat for parents in the United States who do not give consent for using dangerous teratogenic drugs to "treat" the emotional and behavioral symptoms their children have...

portions of this post were originally used in 'What is the Scientific Basis of Psychiatric Treatment?' 12-30-10

Feb 5, 2012

Bioethics of Research with Human Subjects

 Guinea Pigs - Pictures

I have come to realize in the last week or so in particular that what I had thought and believed to be true seem to have little basis in how things are done.  It is knowledge that grieves me.  What is, is.  I don't wish to escape from reality; but I am not  happy when I validate dark suspicions about the nature and the breadth of man's inhumanity to man.   It's better to know than not; but it sure doesn't make me feel any safer.  It further erodes what small bit of confidence in my fellow man I do have.  Some aspects of what is real and what's really going on, seems surreal; truly strange and weird.  Real life has become like the horror and  sci-fi flicks that used to be on TV on Saturday afternoons when I was a kid, I didn't like them either...I always figured real life and real people are scary enough. I still feel that way...
via The Hastings Center:

Rethinking Informed Consent in Research 

"While voluntary informed consent to participate in research has long been an "axiom of bioethics," in reality there has been a "process of erosion and retreat" from this principle, said Alexander Capron in the Beecher Award Lecture on December 2, 2010 in New York. Capron noted the relevance of this trend in light of President Obama's request last month that his bioethics commission examine the ethics of human subjects research."
               

via The New Yorker
DEPT. OF MEDICAL ETHICS

GUINEA-PIGGING by Carl Elliott


 JANUARY 7, 2008  
a couple excerpts:
"As it turned out, the disciplinary action was a response to the injuries or deaths of forty-six patients  under Abuzzahab’s supervision. Seventeen of them had been research subjects in studies that he was conducting. These were not healthy-volunteer studies. According to the board, Abuzzahab had “enrolled psychiatrically disturbed and vulnerable patients into investigational drug studies without ensuring that they met eligibility criteria to be in the study and then kept them in the study after their conditions deteriorated.” The board had judged Abuzzahab a danger to the public and suspended his license, citing “a reckless, if not willful, disregard of the patients’ welfare.”


One case, which was reported in the Boston Globe, concerned a forty-one-year-old woman named Susan Endersbe, who had struggled for years with schizophrenia and suicidal thoughts. She had been doing well on her medication, however, until Abuzzahab enrolled her in a trial of an experimental anti-psychotic drug. In the trial, she was taken off her regular medication and became suicidal. When Abuzzahab gave her a day pass to leave the hospital unsupervised, she threw herself into the Mississippi River and drowned. In another case cited by the board, Abuzzahab had prescribed a “large supply of potentially lethal medications” to a woman with a history of substance abuse, “shortly after a serious suicide attempt.” She committed suicide by taking an overdose.

The public portion of Abuzzahab’s disciplinary file is freely available from the Minnesota licensing board, and has been posted on the Web site of Circare, a watchdog group that documents research abuse. When I ran a Google search on “Faruk Abuzzahab,” the first hit I got was a 1998 article in the Globe on his trial disasters. Yet none of this seems to have derailed Abuzzahab’s research career. Even after his suspension, the Times has reported, he continued to supervise drug trials, and to receive payments from at least a dozen drug companies. In 2003, the American Psychiatric Association awarded him a Distinguished Life Fellowship." (emphasis mine) Read more here

via Mother Jones:

The Deadly Corruption of Clinical Trials

When you risk life and limb to help test a drug, are you helping science—or Big Pharma? One patient's tragic, and telling, story.


an excerpt:
"IT'S NOT EASY TO WORK UP a good feeling about the institution that destroyed your life, which may be why Mary Weiss initially seemed a little reluctant to meet me. "You can understand my hesitation to look other than with suspicion at anyone associated with the University of Minnesota," Mary wrote to me in an email. In 2003, Mary's 26-year-old son, Dan, was enrolled against her wishes in a psychiatric drug study at the University of Minnesota, where I teach medical ethics. Less than six months later, Dan was dead. I'd learned about his death from a deeply unsettling newspaper series by St. Paul Pioneer Press reporters Jeremy Olson and Paul Tosto that suggested he was coerced into a pharmaceutical-industry study from which the university stood to profit, but which provided him with inadequate care. Over the next few months, I talked to several university colleagues and administrators, trying to learn what had happened. Many of them dismissed the story as slanted and incomplete. Yet the more I examined the medical and court records, the more I became convinced that the problem was worse than the Pioneer Press had reported. The danger lies not just in the particular circumstances that led to Dan's death, but in a system of clinical research that has been thoroughly co-opted by market forces, so that many studies have become little more than covert instruments for promoting drugs. The study in which Dan died starkly illustrates the hazards of market-driven research and the inadequacy of our current oversight system to detect them."  (emphasis mine) read the rest here


 Guinea Pig Picture source: CavyMadness © 1999-2003 Nhan and Tammy Rao

LinkWithin

Related Posts Plugin for WordPress, Blogger...

FAIR USE NOTICE: This may contain copyrighted
(C) material the use of which has not always been specifically authorized by the copyright owner. Such material is made available for educational purposes, to advance understanding of human rights, democracy, scientific, moral, ethical, and social justice issues, etc. It is believed that this constitutes a 'fair use' of any such copyrighted material as provided for in Title 17 U.S.C. section 107 of the US Copyright Law. This material is distributed without profit.